For years the phrase dysplastic naevus (dysplastic mole) has been used in clinics with a tone that sounds alarming. Dysplastic naevus is a histological term meaning a mole shows atypical cell features under the microscope. That label suggested to many people that a mole was on a path to melanoma, but the way clinicians use the term is changing. Evidence and expert opinion have shown the label is subjective, can be inconsistently applied, and may do more harm than good by causing unnecessary worry and procedures.
Why the Term Is Losing Favour
The problem with the word dysplastic is that it implies a transitional state, as if a mole is half-way to cancer. In reality, microscopic assessment of moles is not always clear-cut. Pathologists—doctors who read tissue under the microscope—can reasonably disagree about whether a sample is dysplastic or a benign naevus (a mole). When experts do not consistently agree on the definition, the term has limited clinical value and can create confusion for patients and clinicians alike.
Another important point is that many melanomas appear on previously normal skin or as new spots rather than arising from an obvious pre-existing mole. That means a focus exclusively on a single “unusual” mole can draw attention away from the broader task of knowing your skin and looking for new or changing lesions. In short, the label can increase anxiety without reliably improving detection.
Shifting Focus to Overall Risk
Modern skin cancer care emphasises your overall risk rather than fixating on whether one mole is called dysplastic. Naevus count (how many moles you have) and mole size are practical measures of risk because people with lots of moles or several large moles tend to have higher lifetime risk. Other important factors include your history of sunburns, skin type, and family history. For example, fair skin that burns easily and a first-degree relative with melanoma both increase risk.
Understanding your personal risk helps determine how often you should have professional skin checks and what prevention measures suit you. A tailored plan reduces unnecessary excisions while catching real problems earlier. This approach is evidence-based and patient-centred rather than fear-driven.
Practical Advice: How to Protect and Monitor Your Skin
Knowing how to protect your skin and what to watch for is the most useful outcome of moving away from alarmist labels. First, remember that ultraviolet radiation (UV) cannot be seen or felt and is not the same as heat. When the UV Index is 3 or above you should use combined sun protection: protective clothing, a broad-brimmed or legionnaire-style hat, shade, Australian-standard sunglasses, and a broad-spectrum water-resistant sunscreen of SPF50+ applied generously about 20 minutes before going outdoors and reapplied every two hours or sooner after swimming, sweating or towel-drying. For practical tips on how much sunscreen to use and the timing, see our detailed advice on sunscreen application amounts and the 20-minute rule for sunscreen. You might also find it helpful to understand how UVA contributes to ageing and damage at a deeper skin level in our explainer on UVA rays.
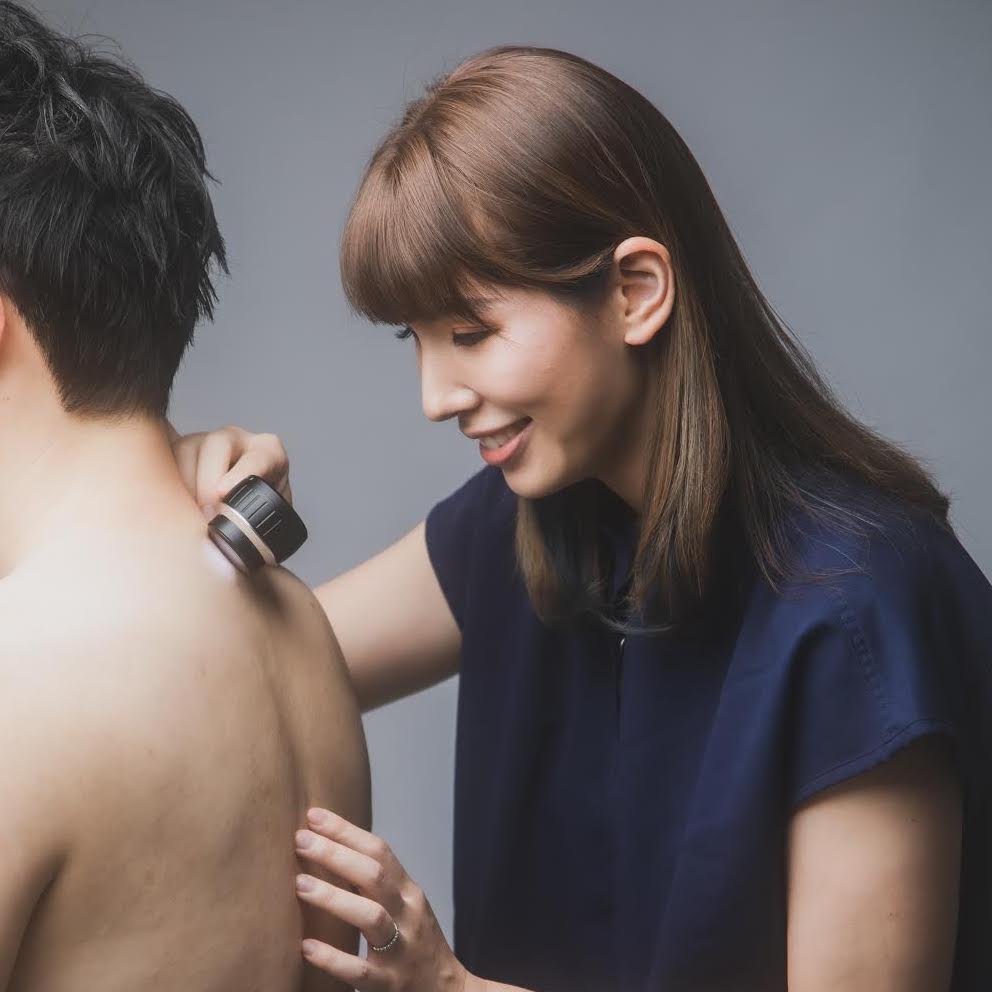
As you monitor your skin, look for outliers: a spot that looks very different to the rest of your moles in colour, shape or size. People often find this ugly-duckling idea the most useful practical rule. If you notice a new lesion, a changing mole, a spot that bleeds or won’t heal, seek a professional assessment. A clinician trained in skin cancer medicine will use dermoscopy (a close-up skin examination tool) and may recommend a biopsy when a diagnosis is uncertain. It is crucial that any diagnostic biopsy or clinical assessment is completed before destructive cosmetic treatments such as laser or cryotherapy are used on an uncertain pigmented lesion, because destroying tissue without a diagnosis can remove important evidence needed to detect and treat skin cancer.
Options, Evidence and When to Consider Medical Prevention
There are effective clinical options for both diagnosis and treatment when needed. Regular professional skin checks provide focused surveillance for people at higher risk and reduce unnecessary excisions. For certain superficial lesions and areas of sun damage, therapies such as photodynamic therapy (a treatment that uses light-activated medication) may be appropriate; discuss suitability with your clinician. We also offer cosmetic mole removal when a lesion is confirmed benign or when removal is clinically indicated.
Some medical prevention strategies have evidence in selected groups. For example, nicotinamide (vitamin B3) has been shown to reduce rates of some non-melanoma skin cancers in people at high risk, but the benefit was measured in specific populations and does not persist after stopping the supplement. Nicotinamide should be considered only after medical advice and as part of an individualised plan; learn more in our overview of nicotinamide and skin cancer. Avoid assuming that supplements prevent melanoma; prevention remains centred on sun protection and professional surveillance.
Take Action for Your Skin Health
Changing terminology does not mean dismissing risk. If you have many moles, a family history of melanoma, or a history of severe sunburn, regular professional checks are sensible. Our clinic provides comprehensive skin cancer checks and, where appropriate, diagnostic or treatment options including photodynamic therapy and cosmetic mole removal. If you have noticed a new or changing spot, or you simply would like an expert review, book an appointment so we can assess your individual risk and advise a plan that respects your priorities and lifestyle. For bookings, visit https://bookings.isoclinic.com.au/.